

The decision nobody wants to sign
The medical director has been putting off the decision for two years. The current system is slow, the vendor's updates have become rare, and the registry export needs manual correction every quarter. Everyone agrees the clinic needs new fertility clinic software. But nobody wants to sign off on a migration while treatment never stops. Patients are stimulating today, retrieving on Thursday and transferring next week. The cryobank holds material from fifteen years ago.
So where is the gap in which you switch?
There isn't one, and you don't need one.
An IVF software migration does not depend on finding a quiet week. It depends on a structured method.
Why IVF software migrations are different
A fertility clinic is not a practice with a patient list. It is a clinic, a laboratory, a cryobank, a quality system and a billing operation, and all of their records are linked. A single embryo record connects to:
- a stimulation cycle and an oocyte retrieval
- a sperm sample and a fertilisation method
- time-lapse annotations and a witnessing chain
- a vitrification event and a straw position
- a consent and a storage fee
- potentially, a registry submission for a specific reporting year
So migrating IVF data means more than exporting tables. It means preserving relationships. Suppose a straw's position is migrated but its link to the original cycle is lost. That is no longer a data quality problem. It is a sample with an incomplete history, which is a serious event in a regulated laboratory.
This is why a structured migration begins with the laboratory and the cryobank, not with the patient master data.
The 5 steps of a structured IVF software migration
This describes the method, not a promised timeline. Every clinic's data has its own history, and a serious vendor assesses it before committing to dates.
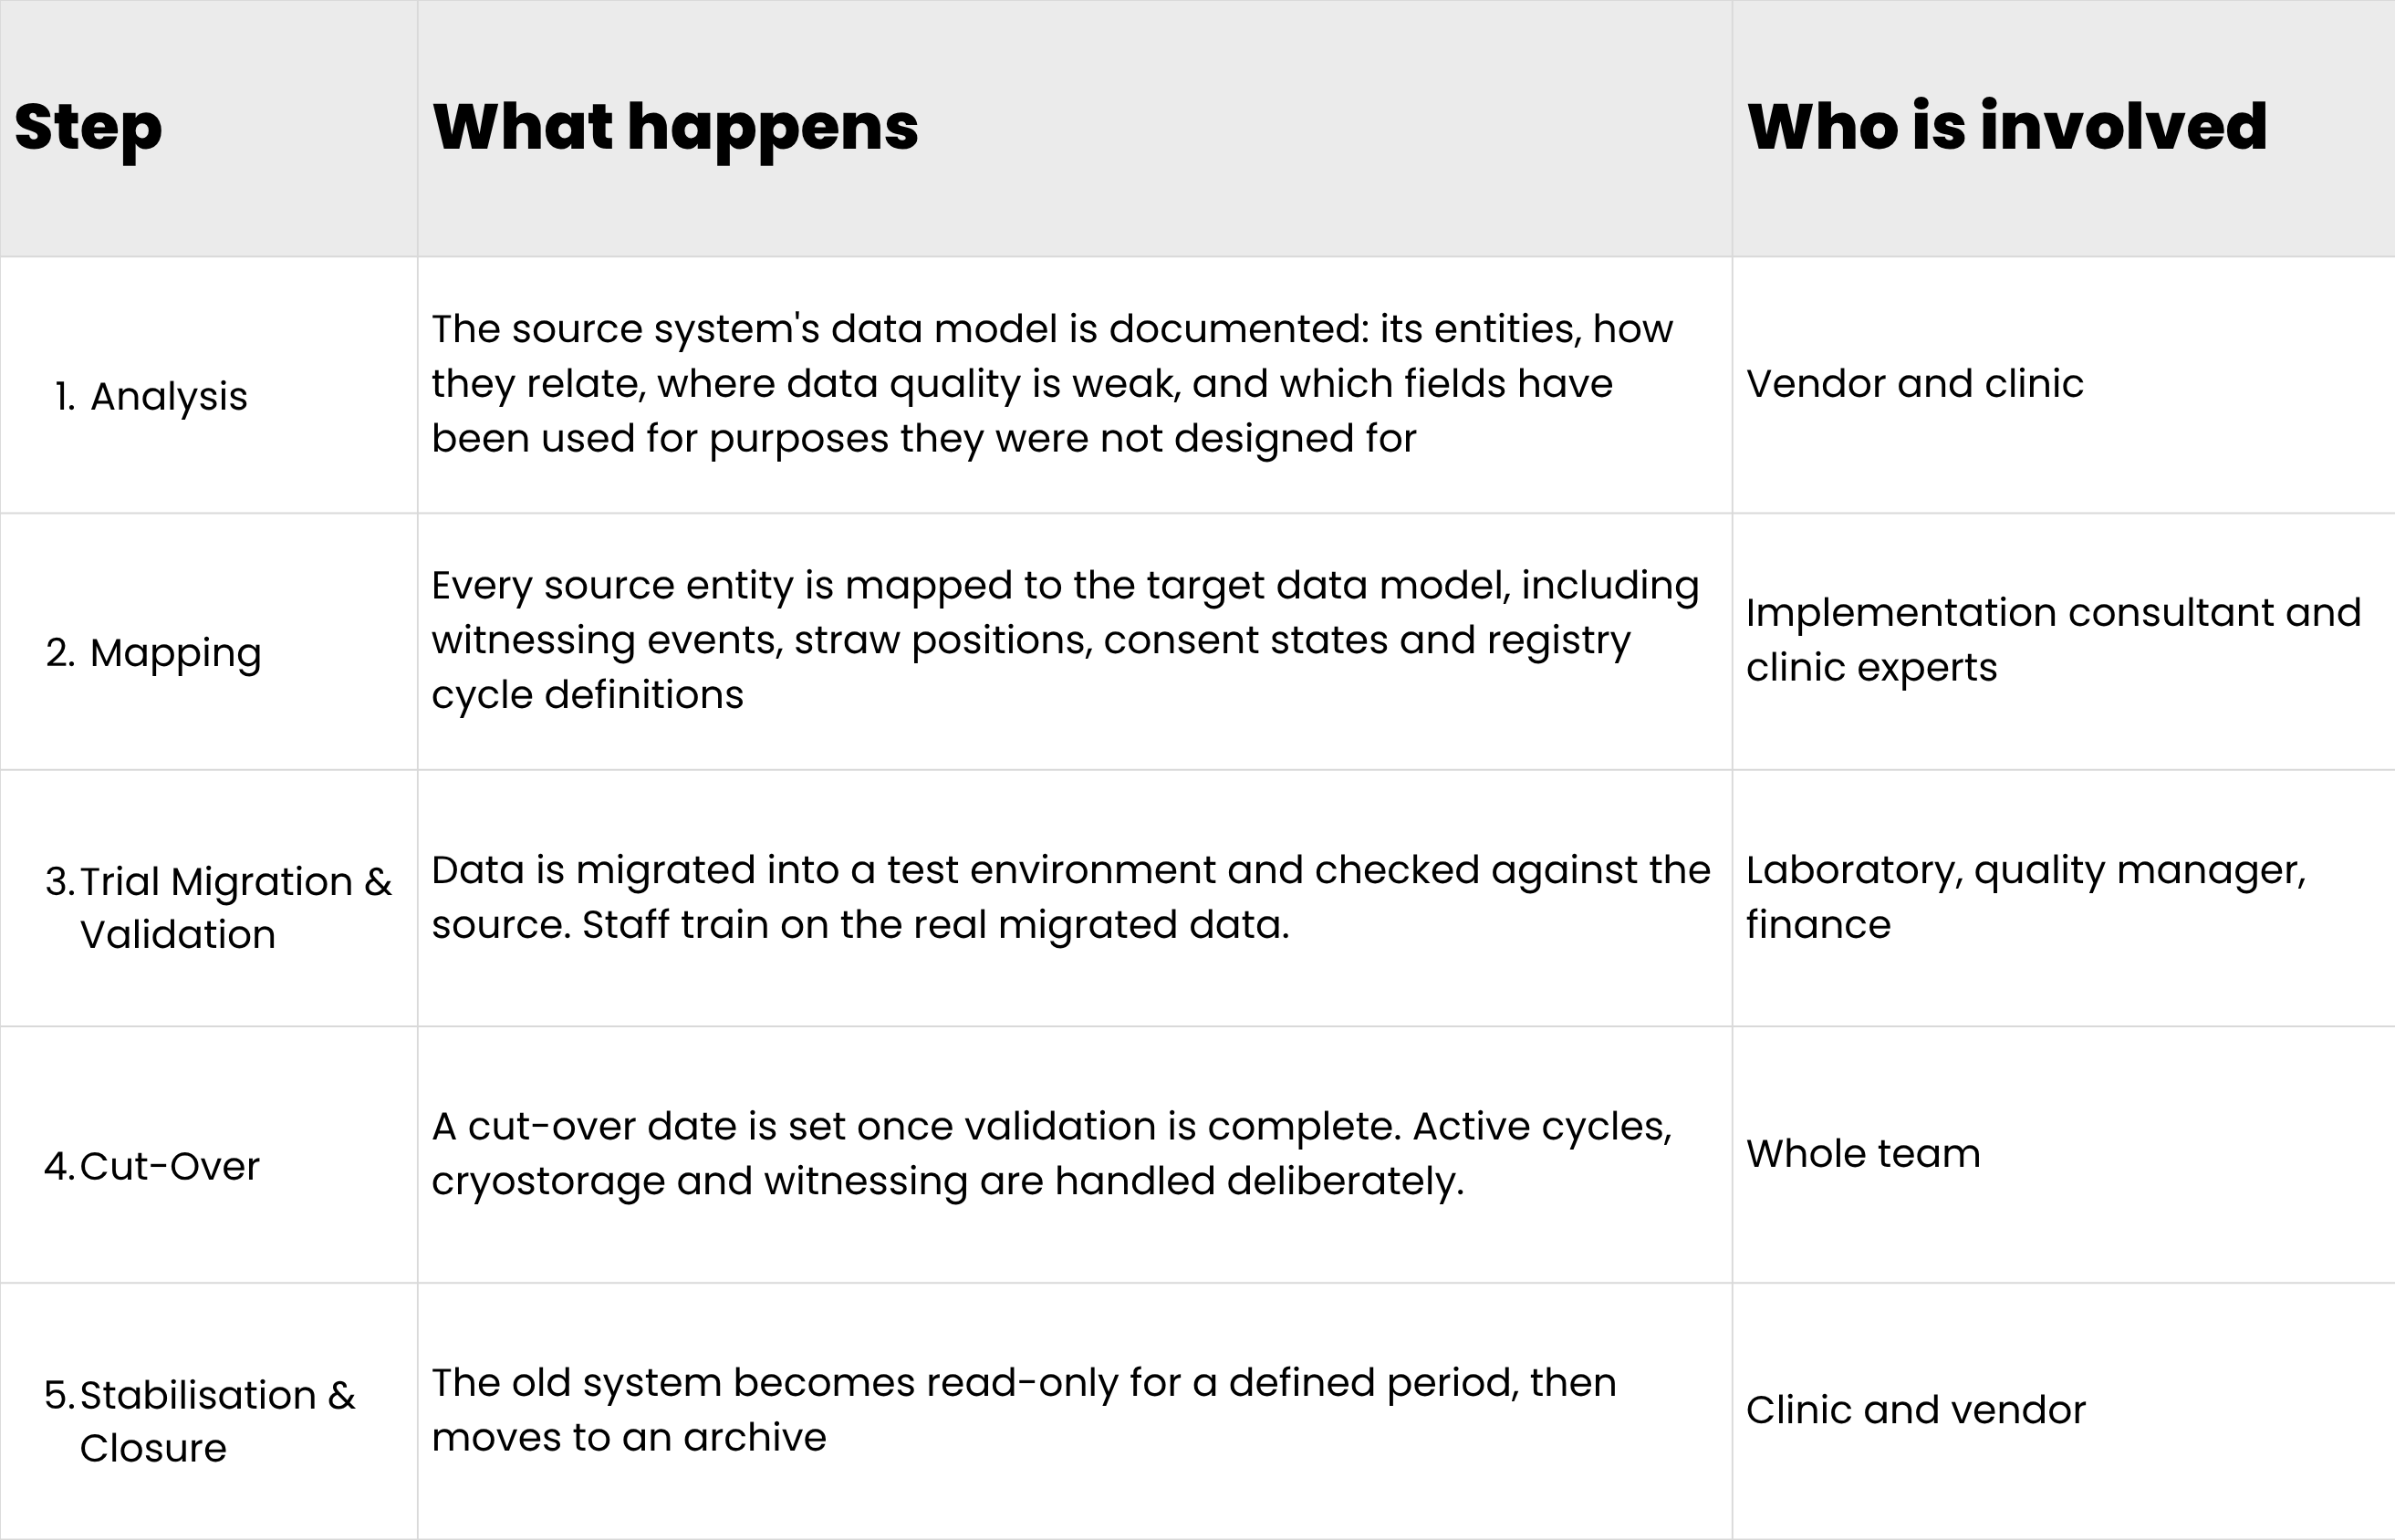
Step 1: Analysis. Every mature clinic has a free-text field that has been quietly carrying critical information for a decade. Finding it now is the difference between a clean migration and a surprise in month four.
Step 2: Mapping. This is where the target system's domain depth shows. If the target already models witnessing events, straw positions, consent states and registry cycle definitions, mapping is a translation. If it doesn't, mapping becomes a compromise, and compromises made during a migration are permanent.
Step 3: Trial migration and validation. In the test environment, each team checks its own area:
- Laboratory: checks a defined sample of cryostorage records, straw by straw.
- Quality management: confirms that the audit history is preserved. If the old system had no audit trail, the migration is documented as the starting point of the new one.
- Finance: reconciles open invoices and balances.
- Registry: exports for a past reporting period are regenerated from the migrated data and compared with what was originally submitted.
Step 4: Cut-over. Active cycles are either completed in the old system before cut-over, or migrated with their full state and re-verified by the team responsible for each patient. Cryostorage is frozen for changes during the final delta migration, then released. Because staff trained on real migrated data rather than demo data, the first day in production looks like the last day of training.
Step 5: Stabilisation and closure. The old system is read-only for a defined period, then archived. There is an end date, and the clinic runs on one data model.
What "without losing a cycle" means in practice
No treatment is interrupted, because the migration is planned around the treatment calendar:
- Retrievals and transfers scheduled across the cut-over are identified early.
- The laboratory agrees which procedures are documented in which system on which day.
- Witnessing continues without a gap, because the new witnessing workflow is live and validated before the first procedure is documented in it.
Why a gradual migration costs more in the end
Some approaches introduce a new portal or scheduling layer on top of the existing system and migrate functions one at a time. It sounds gentler, but the disruption is not avoided. It is spread over a longer period, and the clinic pays for running two data worlds side by side: reconciling them, and explaining to auditors which one is authoritative for which record.
A migration with a defined method and a defined end is not the risky option. It is the one that ends.
What to look for in a target system and a migration partner
Whichever system a clinic chooses, these questions help assess whether a migration will work:
- Is the laboratory fully part of the system from day one? Embryology, andrology, witnessing, cryostorage and quality management should be in the target system at go-live, not added "later". MedITEX IVF, for example, runs embryology, andrology, electronic witnessing, time-lapse integration, cryostorage, quality management with audit trail and CAPA, billing and patient communication on one shared database.
- Does the data model already reflect how the laboratory works? Witnessing events, straw positions, consent states and registry cycle definitions should exist in the target, so that nothing has to be forced into free-text fields.
- Will the vendor sit at the same table? A migration is a joint project. The clinic knows the history of its data, and the vendor knows its target model. It works when the embryologist who knows what the free-text field really means, the implementation consultant who knows how to map it, and the quality manager who signs off the validation work together.
- Has the vendor done this before, and will it still be there in ten years? Experience in the regulated laboratory and a stable company behind the product matter more than any feature list. At MedITEX, this experience comes from nearly 20 years of work with more than 500 fertility clinics in 54 countries, backed by the listed healthcare IT group NEXUS AG.
Conclusion
The question is not whether a fertility clinic can afford to switch IVF software. It is whether it can afford to keep putting off a decision that costs more with every quarter of manual corrections. A structured migration can be led from the laboratory, validated by the people who carry the risk, and completed with a defined cut-over and a defined end. That is how clinics switch without losing a cycle.
Thinking about a change of system? If you'd like an outside view of your data landscape before setting dates, the MedITEX implementation team is happy to take a look.


